
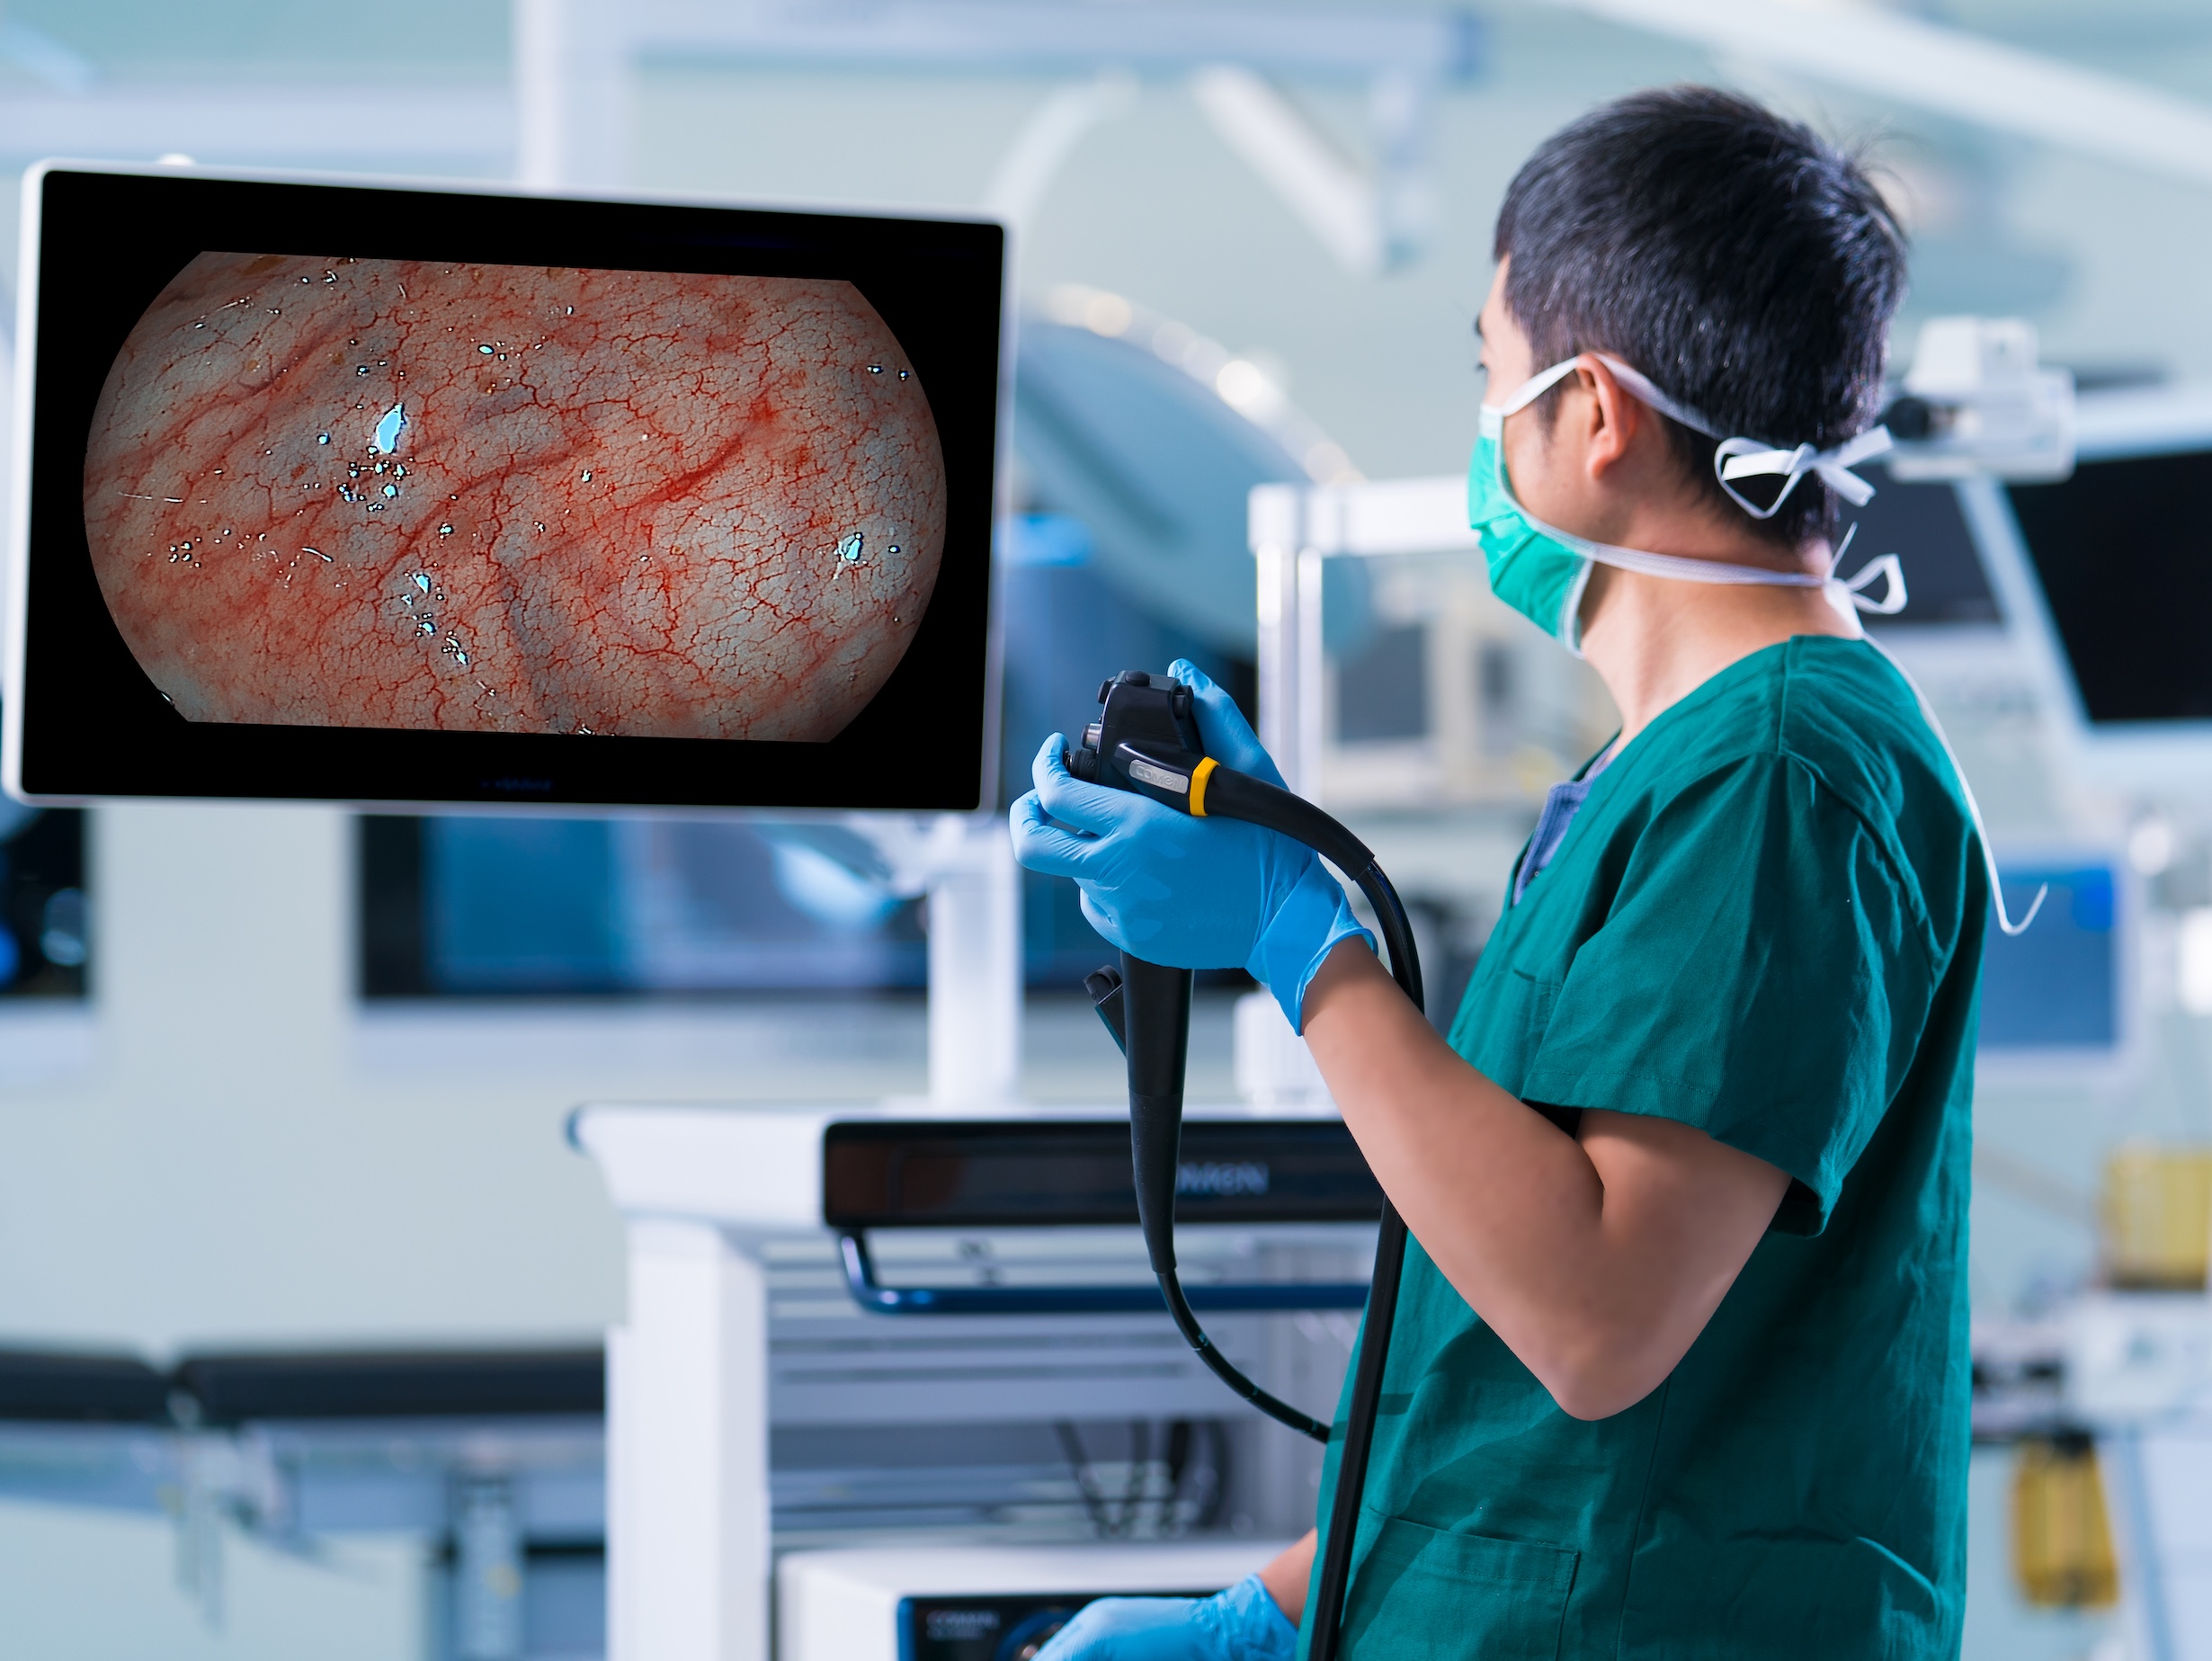
When a Small Lens Breaks a Big Promise
I remember a cramped clinic in Seattle, March 2021: a routine bowel screening, a nervous nurse, and a video colonoscope whose image fuzzed at the crucial turn. In that room I learned how fragile our assumptions about endoscope imaging really are. I have overseen dozens of procurement bids and I still find that the simplest flaw—fogged distal optics, a clogged biopsy channel—creates the deepest delay (and yes, it felt like a betrayal).
Scenario: a three-month audit in my team showed 27% of procedures had at least one image-quality interruption; data: those interruptions increased procedure time by an average of 12 minutes per case; question: how do we stop the cascade before the schedule collapses? I ask that because I live the logistics. I once swapped an LED illumination module at 2 a.m. to keep a unit running through a screening camp in East London; that single swap saved two full clinic days of backlog. I will not romanticize tech—I’m blunt about where traditional solutions fail: fragile optics, single-point failure electronics, and invisible contamination paths. These are not abstract terms to me; they’re costs, delays, and angry patients.
What exactly breaks more often?
From my logs I can point to three recurring culprits: wear on the insertion tube, intermittent CCD sensor dropouts, and inadequate waterproofing at the distal tip. We tracked an uptick in image noise when units were reused beyond recommended cycle counts. I counted—yes, I counted—units used 450 times instead of 300 because budgets were squeezed. That decision had a measurable consequence: a 15% rise in repeat imaging within 30 days.
Forward Steps: Comparing Repair, Redesign, and Procurement
Now I make a firm, forward-looking claim: procurement choices beat miraculous fixes. Compare a repair-first policy with a replacement policy over two years and you will see total downtime and hidden costs diverge dramatically. We modeled three fleets—refurbish-heavy, replace-as-needed, and hybrid—and the hybrid kept throughput highest while lowering infection-risk events. When I evaluate a new video colonoscope, I look for modular distal optics, easily swappable LED illumination, and clear service logs. Those features shorten mean time to repair. Simple. There—I’ve said it.
Technically speaking, prioritize devices with redundant signal pathways and robust sealing at the biopsy channel. I ask vendors for real cycle-life data, not glossy claims: exact device-tested cycles, failure modes observed, and repair turnaround in our region. We negotiated a contract once where a three-day swap policy prevented 80 cancelled procedures in a quarter. Small clauses. Big impact. Wait—these details matter more than a glossy brochure.
What’s Next?
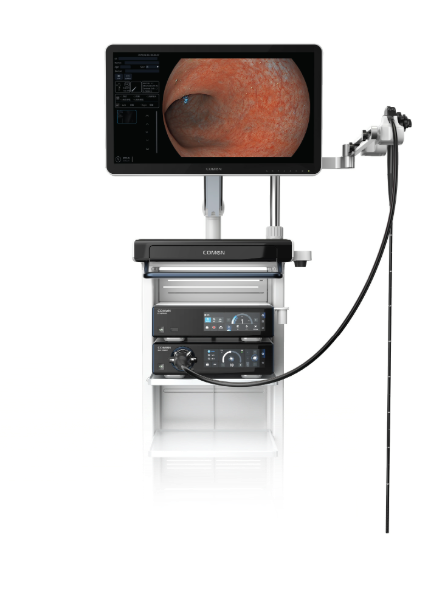
We are moving toward systems that report subtle degradation before the image fails—predictive alerts based on pixel noise trends, automated leak tests, and serviceable distal modules. I expect the next generation to cut unscheduled downtime in half. In practice, that means fewer late clinics, fewer anxious messages to patients, and a procurement model that values serviceability as highly as initial cost. I have seen prototypes in a regional demo (June 2022) and the difference was plain: smoother procedures, cleaner images, and less staff burnout.
How to Choose: Three Concrete Metrics I Use
I will leave you with three metrics I demand in bids—no fluff, no slogans. First, verified cycle-life with real-world counts (not lab-accelerated numbers). Second, median mean-time-to-repair within your postal region. Third, the presence of modular distal optics and documented ease of cleaning. Measure these, and you measure the true cost. Also, ask for a service trial—try one unit in a high-volume week. You’ll see the gap. It’s that simple. Oops—sorry, one more: demand a recorded case of leak-test procedures; I insist on seeing those logs.
I speak from over 15 years moving equipment through hospitals and warehouses, negotiating SLA clauses in Manchester and running field swaps in Barcelona. I write as someone who has been called at midnight and who has stood beside nurses as they trusted a tiny lens to tell them the truth. For honest guidance on procurement that respects real-world failure modes, consider the practical help available at COMEN.
